
Psoriasis
Psoriasis: A Dermatologist’s Guide
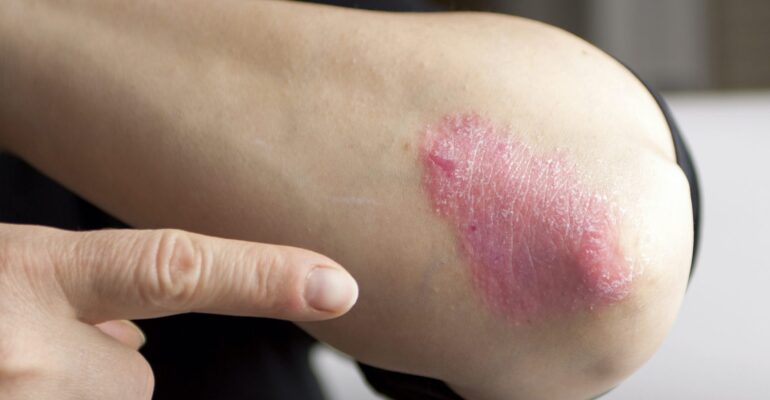
Psoriasis is a chronic, non-contagious, immune-mediated inflammatory skin condition that affects approximately 0.1% to 3% of the global population. It can occur in both males and females of any age, although in India it is more frequently observed in the second decade of life and among individuals of reproductive age.
Causes of Psoriasis
Psoriasis arises from a complex interplay of genetic, immunological, and environmental factors. It involves hyperproliferation of keratinocytes and dysregulation of immune pathways, particularly involving T-cells and cytokines such as TNF-α, IL-17, and IL-23. Common triggers include:
Stress
Infections (bacterial or viral)
Certain medications (e.g., beta blockers, lithium, antimalarials)
Lifestyle factors (alcohol, smoking, obesity)
Environmental factors (cold weather, skin injury)
Who Can Be Affected?
Although psoriasis may occur at any age, there are two peaks of onset:
Early-onset psoriasis (Type I): Before 40 years of age, often with a familial predisposition.
Late-onset psoriasis (Type II): After 40 years, usually sporadic.
Commonly Affected Areas
Psoriasis may appear on any body site, but commonly involves:
Scalp
Elbows and knees
Lower back
Nails
Palms and soles
Genital and intertriginous areas
Signs and Symptoms
Psoriasis presents with distinct clinical features, including:
Red, raised, scaly plaques
Silvery-white scales over erythematous patches
Itching or burning sensation
Nail changes like pitting, onycholysis, or subungual hyperkeratosis
In severe cases, joint pain and swelling suggestive of psoriatic arthritis
Treatment Options
The goal of psoriasis treatment is not cure, but long-term control of symptoms to improve the patient’s quality of life. Management should be personalized based on disease severity, body site involvement, patient preference, and comorbidities.
1. Topical Therapies (for mild disease):
Emollients: Glycerin, petrolatum, and mineral oils improve hydration and skin barrier.
Topical corticosteroids: Anti-inflammatory agents used short-term.
Vitamin D analogues, retinoids, calcineurin inhibitors, keratolytics, coal tar, anthralin: Chosen based on plaque thickness and site.
2. Phototherapy (for moderate disease or special sites):
Narrowband UVB, broadband UVB, PUVA, Excimer laser (308nm): Useful in resistant or widespread psoriasis.
Precautions: Protect eyes, genitals, breasts; avoid if history of skin cancer or photosensitive conditions.
Enhancers: Use of emollients pre-therapy and sunscreens for unaffected areas.
3. Systemic Non-Biological Therapies (for moderate to severe disease):
Methotrexate, Cyclosporine, Mycophenolic acid, Acitretin
Indicated when:
Disease is extensive or unresponsive to topical and phototherapy
Quality of life is significantly compromised
Comorbid psoriatic arthritis or severe distress is present
4. Biologic Therapies (for severe, refractory, or life-threatening disease):
Agents: Adalimumab, Itolizumab, Etanercept, Infliximab, etc.
Indications:
High Psoriasis Area Severity Index (PASI) and Dermatology Life Quality Index (DLQI) scores
Inadequate response or contraindication to conventional systemic therapies
Severe psoriatic arthritis
Note: Biologics should be prescribed only by a qualified dermatologist. Regular monitoring is essential due to potential adverse effects.
5. Lifestyle Modifications
A holistic approach improves treatment outcomes:
Stress management: Yoga, meditation, and relaxation techniques
Healthy habits: Avoid alcohol, quit smoking, maintain a BMI of 18.5–24.9
Timely treatment of infections
Avoid known trigger medications after physician consultation
Duration of Treatment
Treatment duration varies by type and severity of psoriasis. Most patients require 6 to 12 months of regular therapy and monitoring for effective disease control.
Possible Side Effects
While side effects differ by treatment modality, most are preventable or manageable under dermatological supervision. Self-medication is strongly discouraged.
When to Consult a Dermatologist
Seek professional dermatological care if:
Lesions are worsening or spreading
Psoriasis is affecting the face, genitals, or joints
There is emotional distress due to visible plaques
There is no response to over-the-counter treatments
Joint pain or stiffness is present, suggesting psoriatic arthritis
Conclusion: Psoriasis is a lifelong condition that requires comprehensive care and regular follow-up. With the right combination of medical treatments, lifestyle modifications, and psychological support, patients can lead a fulfilling and confident life despite the diagnosis.